

Issue #403: This week, I'm looking at why Zimbabwe rejected US$367 million in U.S. health funding. At first, it seems simple: A rich country offered a poor country desperately needed money, but only under new conditions Zimbabwe considered deeply unfair. What are the effects of a country defending its sovereignty? As always, it's not quite black and white.
Also this week: No more social media in Equatorial Guinea, what people think about democracy in the Americas, Russian soldiers within the army in Myanmar, a Brazilian scholar on far-right memes, a very emotional Syrian superstar homecoming, and so much more.
Editorial closing date: Sunday, September 27, 2026. This newsletter has been edited by Jonathan Ramsay.
The U.S. will end funding for health programs in Zimbabwe by the end of September
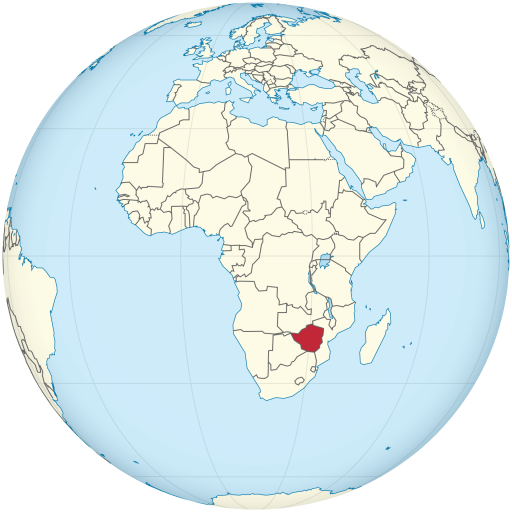
Refresher: For many years, the U.S. paid a lot of money for medicines, clinics, healthcare workers, and disease-prevention programs elsewhere (countries do this not for charity, but for their own benefit; the U.S. was, and still is, the biggest spender worldwide). However, when President Trump returned to office in January 2025, his administration was like, 'hold up, we have to check how much foreign aid is costing us exactly.'
It then came up with a new approach, called the "America First Global Health Strategy." It's not a hard stop to all foreign aid, but the current administration wants the U.S. to pay much less and wants recipient countries to take over more of the cost. Under this strategy, the U.S. negotiates a separate "partnership agreement," directly with each government. Most last three to five years. The exact conditions differ from country to country, but they can include 'this is how much you need to spend so you get the full amount of U.S. funding' and possible penalties if a country misses those targets, access to health data, buying more from U.S. companies, etc. So far, 35 countries have signed agreements, most of them in Africa. The full texts are not publicly available in every case, which makes it difficult to compare all the conditions properly. Zimbabwe is one of the countries that said, "Nah, not under those terms."
What happened:
The United States offered Zimbabwe a new five-year health "partnership agreement" worth about US$367 million, but attached conditions Zimbabwe considered 'nah'. The U.S. then said, 'fine, we're out then', and decided not to renew its existing health programs after September 30, 2026.
Why this matters: Zimbabwe is one of the first countries to face the consequences of the new U.S. strategy of tying health aid to "partnership agreements." With less and less development money coming in to support Africa in general, in recent years, critics are saying, 'You cannot destroy much of the existing system first, then give very poor countries only three to five years to replace billions of dollars.'
Tell me more:
The money would have supported a lot (the U.S. has been Zimbabwe's biggest health donor for decades). There's now less money coming in for HIV/AIDS treatment and prevention, tuberculosis and malaria programs, maternal and child health, laboratories and disease surveillance, and preparation for future outbreaks.
The new U.S. strategy also expected Zimbabwe to pitch in more and more of its own money, so that they would no longer be dependent on U.S. support in the future. 'We've given Zimbabwe almost US$2 billion in health assistance since 2006,' the U.S. said.
Why did Zimbabwe reject it?
The conditions to that proposed "partnership" seemed a bit icky to Zimbabwe's government. The central dispute was access to health information and biological materials. According to Zimbabwe's government, the U.S. wanted more access to epidemiological information, sensitive health data about Zimbabwean citizens, virus samples, and other biological resources.
Zimbabwe was like, 'okay, and what would we get in return?' The "partnership" did not guarantee any access to vaccines, diagnostic tools, or treatments subsequently developed using the Zimbabwean data. The U.S. position is that 'sharing is caring. It's good to know these things so we can all be a bit safer.' However, the agreement did not mention that the U.S. would share their health data with Zimbabwe, too. 'How fair is that?' asks Zimbabwe's President Mnangagwa.
BTW: The entire agreement is not publicly available. Both governments have talked about it here.
My take: It's easy to paint a very black-and-white picture here: U.S. bad, Zimbabwe sovereign. Many different things could be true at the same time. The U.S. may be exercising neocolonial power here although its funding still accomplished some good, while Zimbabwe's own government may have failed to build a health system that is capable of resisting that pressure. And perhaps Zimbabwe may have had limited room to become self-sufficient because colonial extraction did not end with independence. And still, rejecting or accepting an unfair agreement can harm ordinary people.
How does Zimbabwean media talk about this?
The Herald frames this decision: 'Zimbabwe protected its sovereignty.'
The Zimbabwe Independent is more critical: 'Sure, there were legitimate concerns, but walking away was dangerous. You put millions of Zimbabwean lives at risk.'
Good to know: Technically, all of this health data sharing could be organized and managed through something that already exists: the World Health Organization. But the U.S. withdrew from the WHO in January 2026, so they're now looking to strike more country-to-country-access deals instead.
What does "funding will end" actually mean?
It doesn't mean that all hell will break loose on October 1. Zimbabwe still has medicine, and its support system isn't reliant on the U.S. only. But this "will trigger a public health catastrophe," says Asia Russel, executive director of Health GAP, an international advocacy group. The U.S. paid for much more than the medicines themselves. It also supported the staff who test patients, laboratories that monitor treatment, and much else.
Dig deeper: Interruptions in HIV care are particularly dangerous. One U.S.-funded HIV project, for example,...
Please log in or subscribe for free to continue reading this issue.
We could use your help to make this issue better. Take a look at the requests below and consider contributing:
- Submit a piece of artwork for this issue
- Submit a news, academic or other type of link to offer additional context to this issue
- Suggest a related topic or source for future issues
- Fix a typo, grammatical mistake or inaccuracy
Below you'll find some of the sources used for this issue. Only sources that support "media embedding" are included.
-
Read the Fact Sheet The America First Global Health Strategy outlines a comprehensive vision to make America safer, stronger, and more prosperous. It will protect the homeland by preventing infectious disease outbreaks from reaching U.S. shores; strengthen our bilateral relationships by entering into multi-year, bilateral agreements that require co-investment from recipient governments, saving millions of lives and […]
-
The deadliest Ebola outbreak on record in the Democratic Republic of Congo may have begun months before it was first declared in May.
-
Facebook and TikTok have been inaccessible in Equatorial Guinea for more than two weeks following the circulation of a video accusing the country’s
-
South Africa police have cautioned against assuming that all the killings are linked but many women are afraid.
-
The governement is exploring the use of nuclear and isotopic techniques to improve agricultural productivity, food safety and resilience to climate...
-
The AmericasBarometer is one of the world's most comprehensive sources of data on democratic governance and public opinion — two decades of evidence, data from dozens of countries, and hundreds of thousands of voices. Since 2004, LAPOP Lab has used the survey to help researchers, policymakers, and civil society understand
-
The process, convened under the U.N. Convention on the Law of the Sea, follows Thailand’s revocation of a 2001 MoU governing bilateral maritime talks.
-
Nairobi and Munich to host 2029 and 2031 World Athletics Championships | PRESS-RELEASES | World AthleticsNairobi and Munich have been selected to host the 2029 and 2031 World Athletics Championships, respectively, following one of the strongest bidding processes in the history of the sport’s flagship event.
-
Sheinbaum’s security strategy has lowered murder rates but should address rampant extortion and disappearances and seek stronger federal-state cooperation.
-
Activists in Cape Town demand a national moratorium on AI data centers, warning that massive expansion by Microsoft, Amazon, and Equinix threatens scarce water and power resources.
-
Accessibility isn't an add-on. In Rwanda, filmmakers are discovering that telling better stories starts by including audiences who have long been left out of the cinematic experience.
-
Off Namibia's desert coast, a company is growing giant kelp in a large underwater farm. The project claims wider benefits for marine life, carbon storage and local jobs.
-
Entrevista de Ita María a la escritora mexicana Dahlia de la Cerda, autora de Perras de reserva, Desde los Zulos y Medea me cantó un corrido.
-
Interventions from the Global South | Viktor Chagas - Humor as hate and humor as hegemonic subversionIn this episode, Professor Mohan Dutta speaks with Professor Viktor Chagas on humor in Brazilian politics. Professor Chagas offers a humor lens to Brazilian independence from Portugal, pointing out...
-
Olu Jacobs : The making of a timeless Brand. On September 16, 2026, Nigeria lost Oludotun Baiyewu Jacobs at the age of 84. The announcement
-
But the military's overall use of AI seems to be accelerating.
Each week, What Happened Last Week curates news and perspectives from Asia, Africa, and the Americas. The newsletter is written by Sham Jaff and focuses on stories that rarely receive sustained attention in Western media.
Read the free edition every week. VIP subscribers receive additional stories, recommendations on what to watch, read and listen, and more.